We run early-phase trials for emerging sponsors at the level a large sponsor would — design, endpoints, analysis, regulatory strategy, execution. Not software for running a CRO, but a new kind of CRO.
The problem
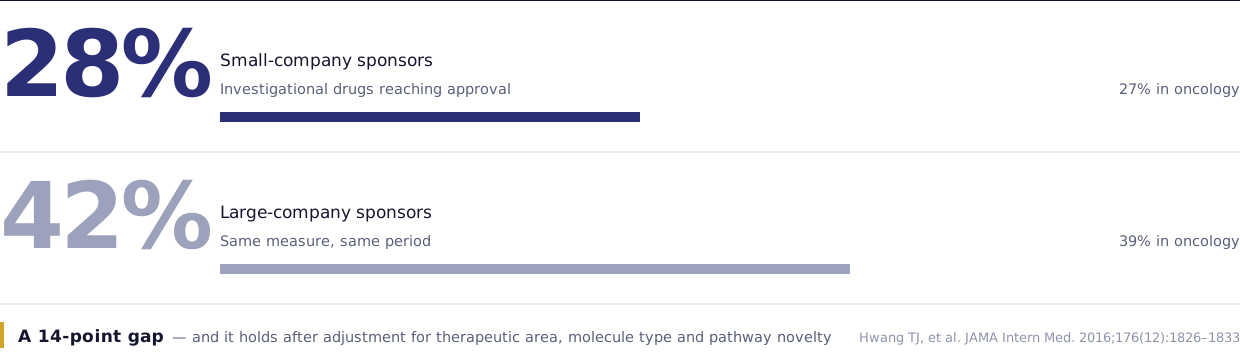
A large sponsor employs statisticians, programmers and data engineers full time and spreads them across dozens of trials. A biotech running one trial cannot justify a single one of those hires. So every question goes out to a consultant, one question at a time, and the answer comes back weeks later — by which point the decision has usually already been made.
What we do
Two kinds of company serve this market, and neither does both jobs. Software vendors build the systems but never run a trial. CROs run the trial but license their systems from someone else, and have neither the engineering capacity nor any commercial reason to extend them.
License platforms to the organisations that run trials, and never operate a study themselves. Their analytical layer sits at maximum distance from the work.
Execute the trial, but license their systems from someone else. Expertise scales with headcount, so the economics are bounded by what an FTE bills.
Operates the study on systems it builds and owns. Work a conventional CRO staffs with hours is delivered by software — and it improves with each study.
Who it changes things for
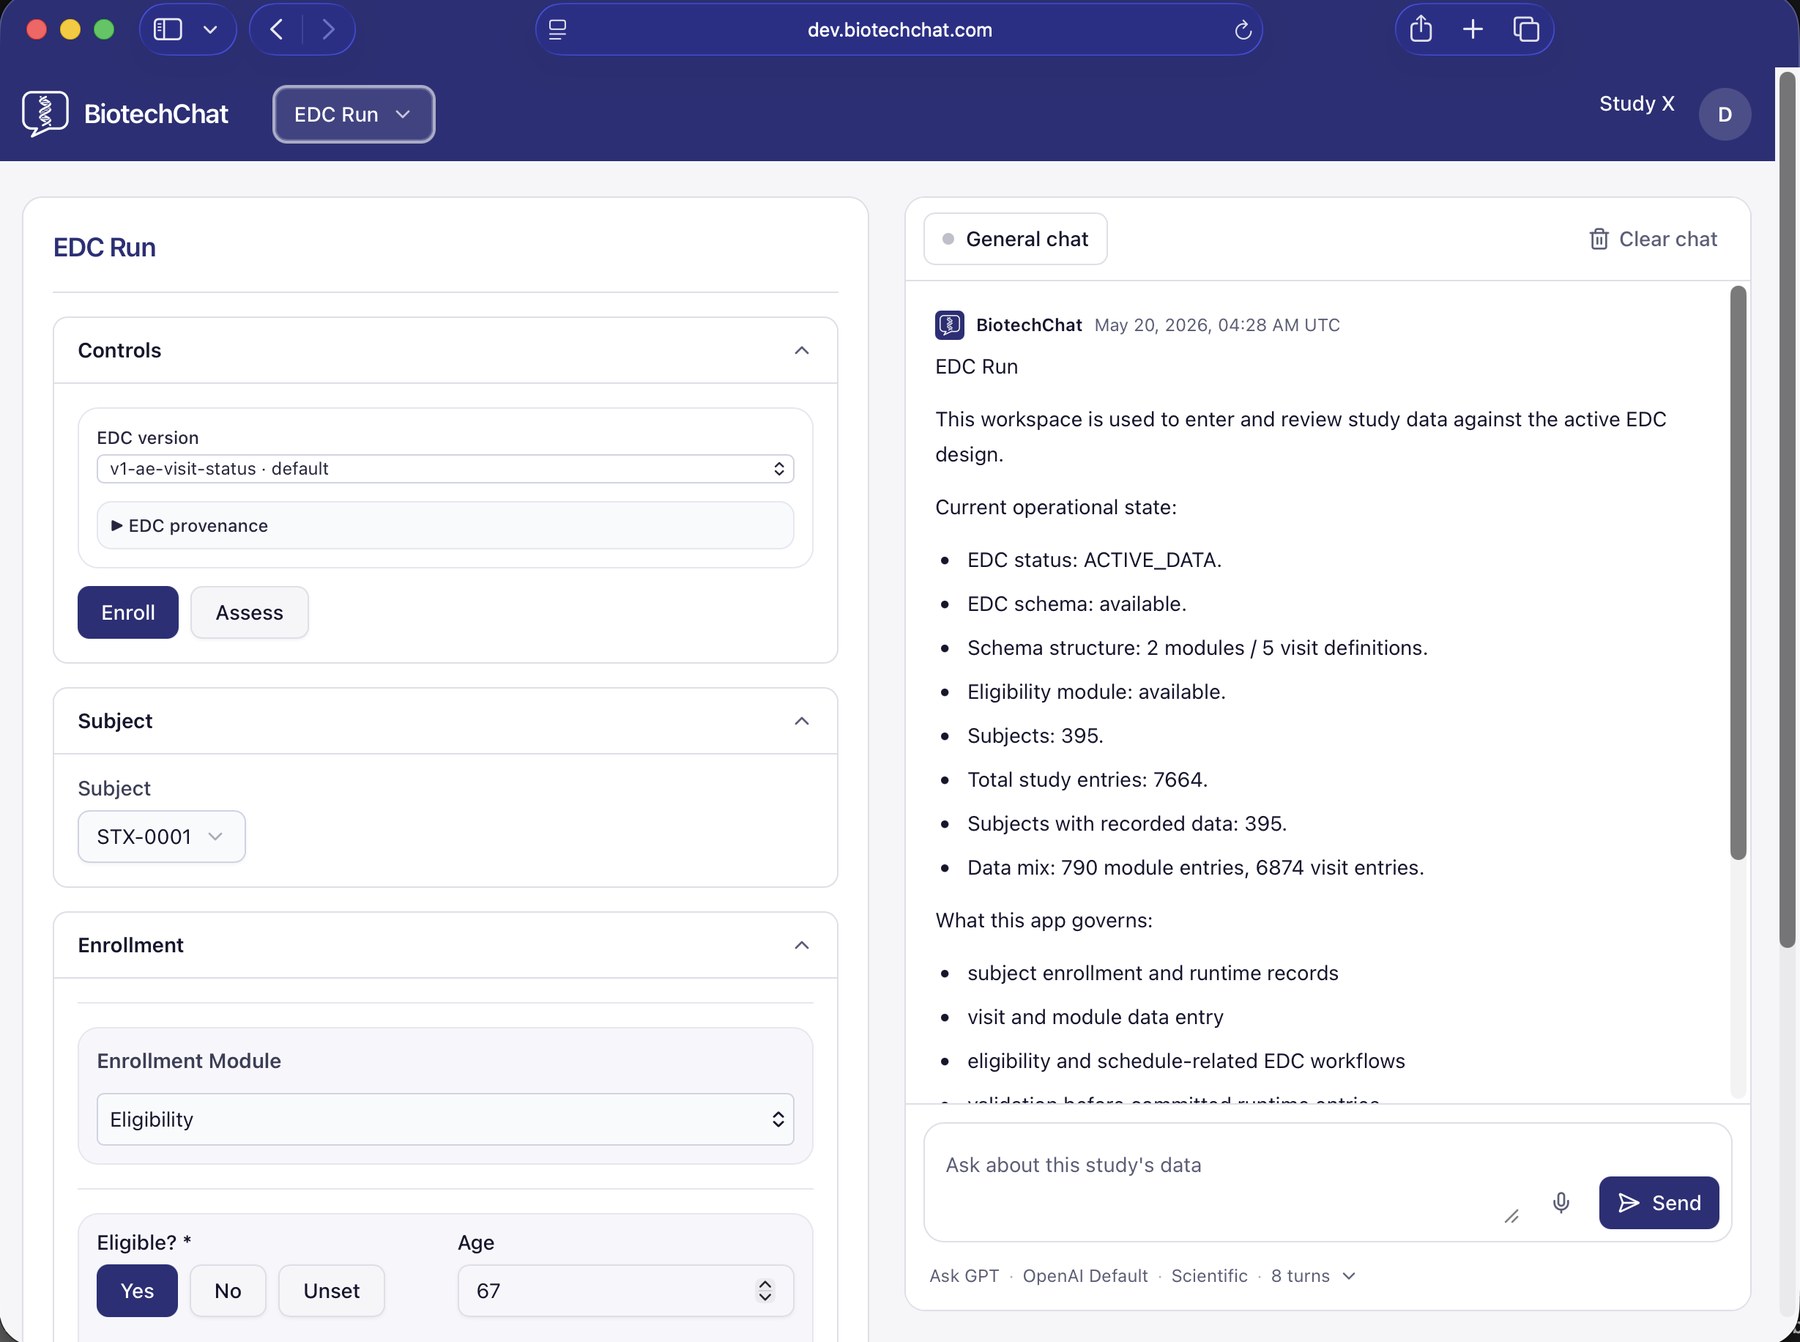
A trial is run by people who each hold one part of it, and most of their week goes on reconciling someone else's export. They all work from the same record here.
| Role | Today | With Sarivera |
|---|---|---|
| Sponsor CEO and program lead | Burn and accrual arrive a month late, in a status deck someone else assembled from the CRO's invoices, and enrolment is a number with no cost attached to it. | Spend against budget, site payments and accrued cost are read off the same record as enrolment, so progress and what it cost are one answer, today. |
| Investigator | The protocol is a PDF you scroll through, and answering "does this subject qualify" means holding three documents in your head at once. | The protocol is a structured artifact you can search and ask questions of, alongside ClinicalTrials.gov, FDA guidance and approved labels. |
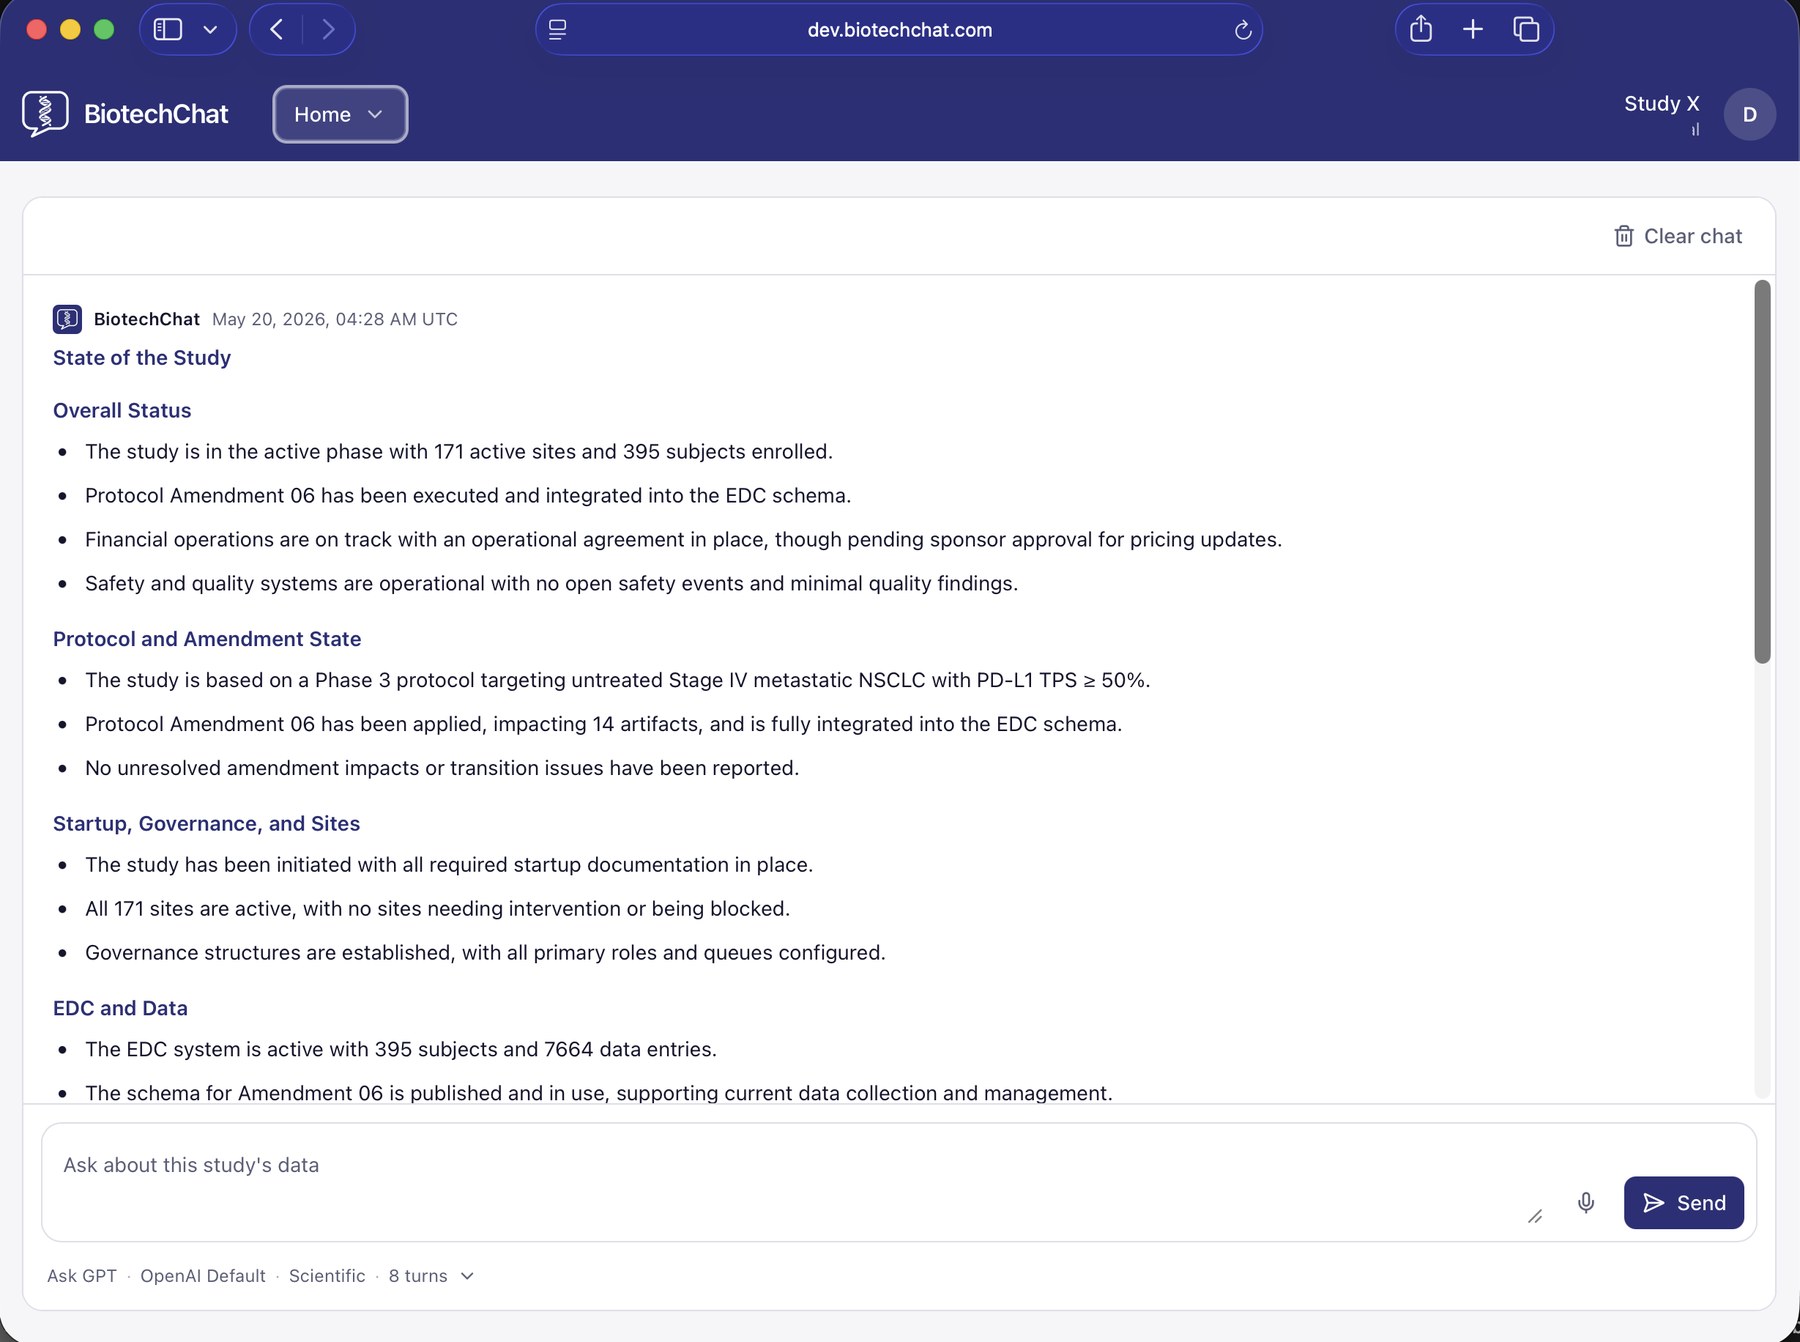
| Clinical operations | The study runs across an EDC, a CTMS, a safety database and a payments spreadsheet, and the first honest picture of the week is whatever comes out of reconciling them. | Enrolment, queries, monitoring, deviations and site payments are one state, so the picture is current without anyone assembling it. |
| Regulatory | An inspection question sends you hunting for which version of a document was in force and who approved it, through email and a document system. | Every artifact is versioned, hashed and attributable, so the answer comes out of its lineage instead of a reconstruction. |
| Quality | A deviation surfaces weeks after it happened, and tying it back to the protocol version in force takes longer than resolving it. | Findings sit against the data and the protocol version they came from, so the trace is already there. |
| Safety | The safety database is a separate system, so an event is entered twice and the two copies have to be matched before anyone trusts either. | A safety event is linked at capture to the subject, the visit and the protocol version in force. |
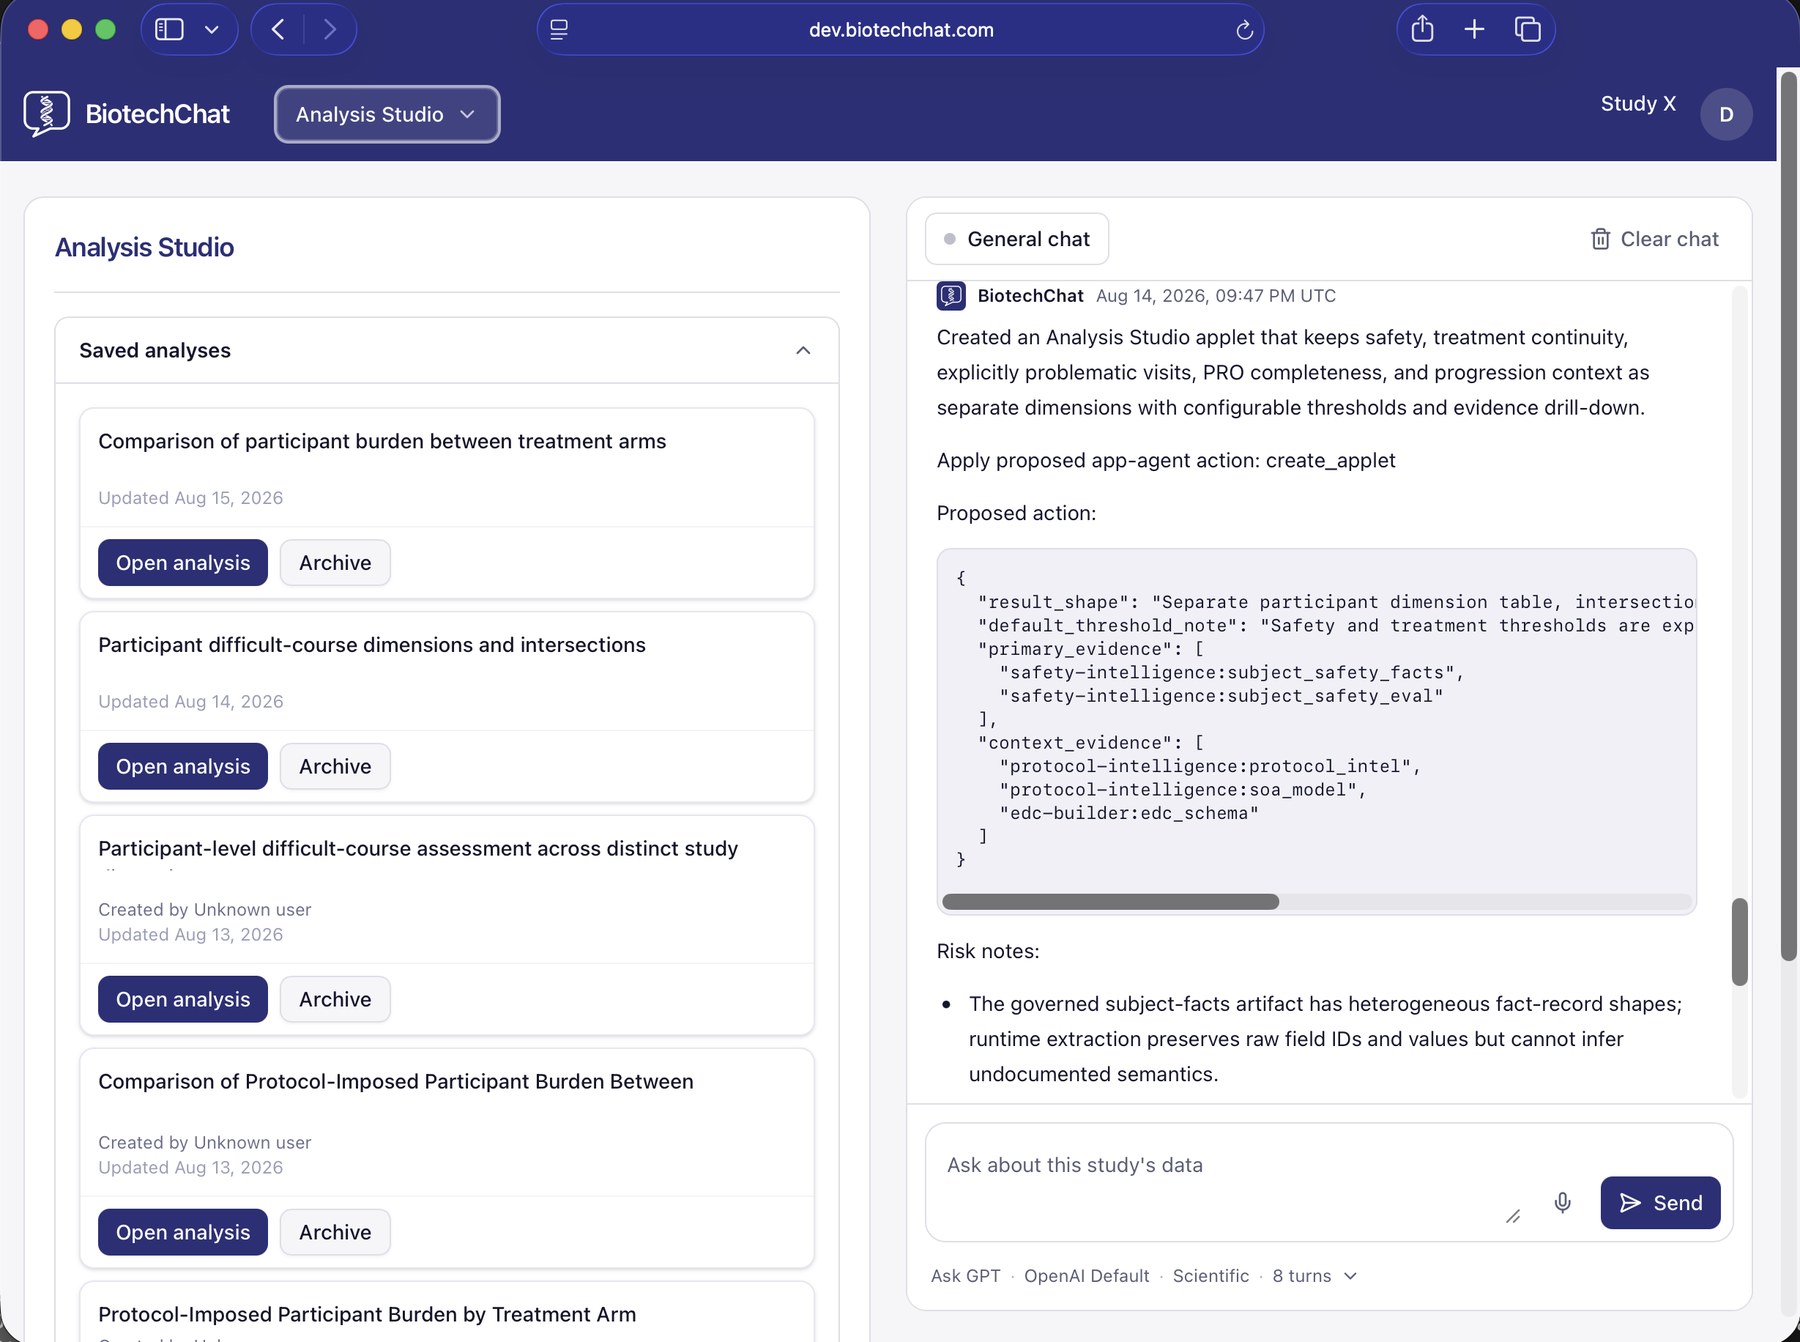
| Biostatistics and programming | Every question means a new extract, a new program and a wait, and the decision is usually made before the answer lands. | Analysis runs on governed data during conduct and re-executes against the same versioned snapshot. |
| Site coordinator | Data is entered, then fails checks weeks later, and an amendment arrives as new forms, new windows and a budget that lags behind them. | Entry is validated before it commits, and an amendment updates forms, visit windows and site budgets together. |
How a trial runs
Every stage of the study, who touches it, and what it writes to.
Your own people. No intermediary, no ticket.
One system. We build it, we run it.
Generated from the protocol
The platform
The hard part was never the AI. It is the governance underneath it.
Alongside the study's own governed data, the platform reads ClinicalTrials.gov, FDA guidance and approved drug labels, so a question about how this design sits against the field is answerable in the same place. Those answers are retrieval over public documents, not analysis bound to a snapshot. The distinction is deliberate, and the system states which it is giving you.
Every governed artifact is versioned, hashed, and traceable to its source and its full history.
Agents propose. Deterministic executors apply. The model never gets the last word.
Every operation is read against the protocol version in force at the time. History stays history.
21 CFR Part 11 electronic-signature and approval workflows, and subject-identifiable source-document QA. Both are in progress and neither is done.
We know exactly what is built and what is not, and we would rather you heard it here than found it in diligence.
Who
I have run clinical development three times from companies that could not afford a clinical development department. At GigaGen I designed and ran the first in-human study of a drug class that had never been in a person before, with a team that would have fit around one table.
At GigaMune I watched science I still believe in stall — not because it was wrong, but because getting it into the clinic cost more than a company our size could carry. That is the more common ending, and it is rarely the molecule's fault.
I built this because I kept hitting the same wall, and because the wall is made of work that software should be doing.
The entry point is a request for proposal on a specific early-phase study. We return a demonstrated study build against your draft protocol in days rather than the weeks a conventional CRO takes to return a bid.
[email protected]